Dr Al-obaidi combines specialist expertise in spinal and musculoskeletal imaging with image-guided intervention. This allows scan findings, clinical assessment and precise procedural planning to be considered as one connected pathway.


Consultant-led procedures for selected joint, tendon, bursal and nerve-related pain, including peripheral nerve blocks, headache interventions and targeted treatment for some forms of persistent pain after surgery.
See
Soft tissues in real time
Plan
A safe needle route
Guide
Medication to the target
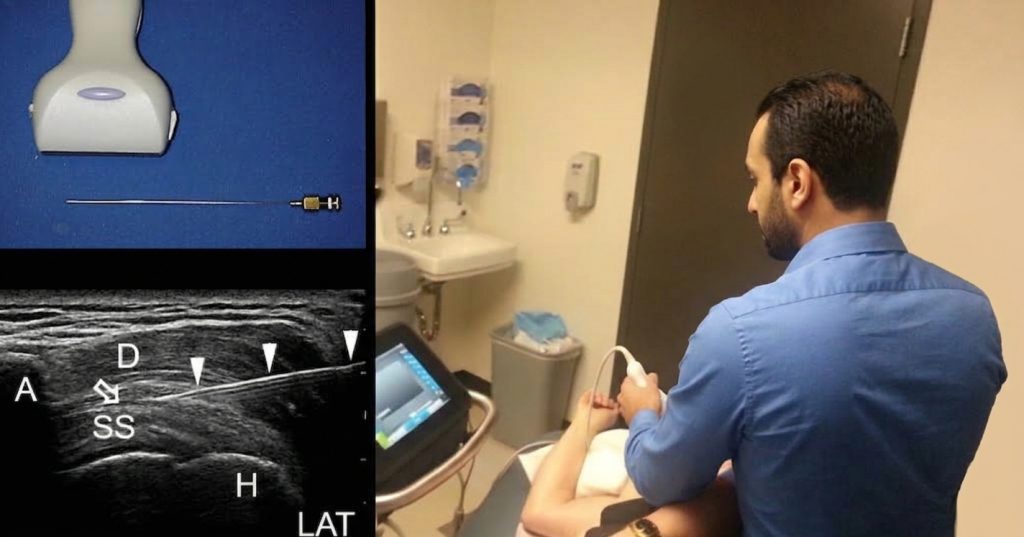
Ultrasound uses high-frequency sound waves to create moving images of muscles, tendons, ligaments, bursae, joints, nerves and other soft tissues. It does not use X-rays.
The consultant can examine the area, plan a suitable route and watch the needle advance towards the intended target. This is particularly valuable when important tendons, nerves or blood vessels are nearby.
The procedure is based on visible anatomy rather than surface landmarks alone.
Its course can be adjusted while avoiding nearby structures where possible.
Medication or fluid is delivered to the selected joint, bursa, tendon sheath, tissue plane or nerve region.
More than one type of injection.
Ultrasound can also guide treatment around peripheral nerves and within tissue planes. These procedures are considered only when the pain pattern, examination and relevant investigations support a specific target.
Targeted treatment within selected joints, including the shoulder, hip and knee, when the clinical findings and imaging support this approach.
Medication is guided into an inflamed or painful bursa, such as the subacromial, trochanteric, ischial or other accessible bursae.
Selected treatment around a tendon or within a tendon sheath. Medication is not deliberately injected into the tendon substance.
Fluid is introduced into the shoulder joint to distend the tight capsule in selected patients with frozen shoulder, usually alongside rehabilitation.
Also called barbotage, this procedure uses ultrasound guidance to needle and wash selected calcium deposits within a shoulder tendon.
Fluid may be sampled or drained from selected joints, bursae or cystic lesions when appropriate, sometimes followed by targeted treatment.
Beyond joints, tendons and bursae.
Ultrasound can also guide treatment around peripheral nerves and within tissue planes. These procedures are considered only when the pain pattern, examination and relevant investigations support a specific target.
Occipital nerve blocks may be considered for selected neuralgia, cervicogenic headache or other headache presentations after clinical assessment.
Selected headache and scalp pain
Local anaesthetic, sometimes with corticosteroid, can be placed around a selected peripheral nerve to reduce pain or assess whether that nerve contributes to symptoms.
Diagnostic or therapeutic nerve treatment
For selected nerve entrapment, fluid may be introduced around a nerve to separate it from surrounding tissue and improve the tissue plane. Suitability depends on the site.
Selected nerve entrapment and neuropathic pain
Targeted injection may be considered for pain from an injured or trapped nerve, scar, neuroma or abdominal wall structure.
Selected nerve entrapment and neuropathic pain
Selected ilioinguinal, iliohypogastric, lateral femoral cutaneous, transversus abdominis plane or rectus sheath procedures may help manage focal abdominal, groin or pelvic wall pain.
Including selected pain after surgery
Selected intercostal or superficial chest wall nerve blocks may be considered for well-localised neuropathic pain, including persistent pain after thoracic or chest wall surgery.
Careful assessment and imaging review
A targeted block around the suprascapular nerve may be considered for selected persistent shoulder pain, particularly when pain limits movement or participation in rehabilitation.
Selected chronic shoulder pain
Depending on the pain pattern, ultrasound may guide selected blocks around superficial sensory nerves or articular nerve branches as part of a broader pain management plan.
Individual assessment required
Select a region to see examples. The final treatment choice depends on clinical assessment and relevant imaging.
Ultrasound can assess the rotator cuff, bursae, biceps tendon and accessible joints, then guide treatment to the selected target.
A straightforward procedure, carefully planned.
Your exact experience will depend on the target and treatment. Most ultrasound-guided injections are performed using local anaesthetic without sedation.
Symptoms, medicines, allergies and consent are checked.
The anatomy and intended target are reviewed.
You are placed comfortably for safe access.
The skin is cleaned and local anaesthetic used if needed.
The needle is watched as it reaches the target.
You receive procedure-specific aftercare advice.
Please read your appointment information and tell the clinic if your health, medication or planned surgery has changed.
Bring an up-to-date list, including anticoagulants, antiplatelets and previous reactions to medicines, dressings or antiseptics.
Corticosteroid can temporarily increase blood glucose. Tell us how your diabetes is managed.
Contact the clinic if you have a fever, skin infection near the injection site, are taking antibiotics or feel unwell.
Tell us if you are pregnant, may be pregnant or are breastfeeding so medication choices can be reviewed.
If you are awaiting an operation in the same region, tell both the clinic and your surgical team before having a corticosteroid injection.
Potential benefits, with realistic expectations.
An injection is one part of treatment. Its value is judged by what it helps you do, not simply by whether the procedure can be performed.
No injection can guarantee complete or permanent pain relief. Expected benefit, alternatives and the role of rehabilitation will be discussed before treatment.
Most patients have no serious complication. The exact risks vary with the target, medicine and your health, and will be discussed before you consent.
Temporary soreness or a flare of pain can occur after treatment. Serious complications are uncommon, but prompt assessment matters if warning signs develop.
Pain, bruising, bleeding or a temporary post-injection flare.
Increasing heat, redness, swelling, fever or feeling unwell needs urgent review.
Skin thinning, colour change or local fat loss can occur after corticosteroid.
Tendon weakening or rupture is uncommon but possible, particularly in vulnerable tendons.
Temporary numbness or weakness can occur. Nerve irritation or injury is uncommon but possible.
Flushing, sleep or mood disturbance and a temporary rise in blood glucose.
Some targets have additional risks. For example, chest wall or intercostal procedures carry a small risk of pneumothorax.
The procedure may not reduce pain or improve function, even when accurately performed.
severe or rapidly increasing pain, fever, spreading redness, marked swelling, persistent new weakness or numbness, breathing difficulty, or signs of a serious allergic reaction.
You will receive advice matched to the procedure and the structure treated. Mild soreness can occur after the local anaesthetic wears off, and corticosteroid benefit may take time to become clear.
If local anaesthetic causes weakness or numbness that could affect control of a vehicle, you must not drive until it has fully resolved. Follow the specific instructions given by the clinic.
Activity recommendations differ between joints, tendons and other targets.
Use the pain relief and local measures recommended to you.
The injection often works best as part of a planned recovery programme.
Use the contact and emergency advice supplied after treatment.
Specialist imaging and intervention in one appointment.
The same consultant brings together the clinical problem, ultrasound findings and procedural plan.

Dr Al-obaidi combines specialist expertise in spinal and musculoskeletal imaging with image-guided intervention. This allows scan findings, clinical assessment and precise procedural planning to be considered as one connected pathway.
Questions, answered clearly.
These answers are general. Your consultation and appointment information will provide advice specific to your procedure.
You may feel a brief sharp sensation or pressure. Local anaesthetic is used when appropriate. Some targets are naturally more sensitive than others, and you can tell the clinician if you are uncomfortable.
Timing varies with the procedure. Allow time for review, consent, scanning, positioning, the injection and aftercare discussion. More complex procedures such as hydrodilatation or barbotage can take longer than a simple injection.
Not always. Existing imaging is reviewed where relevant, and the target is assessed with ultrasound at the procedure appointment. Sometimes further imaging or a separate diagnostic assessment is needed before treatment.
Local anaesthetic may give an earlier temporary change. Corticosteroid benefit, if it occurs, is not always immediate and can take several days to become apparent. Some patients do not obtain meaningful relief.
There is no reliable single answer. Benefit may be short-lived, last for a useful period, or not occur. The diagnosis, condition of the tissue and rehabilitation plan all matter.
This requires an individual assessment based on the medicine, dose, reason for treatment and proposed target. Do not stop anticoagulant or antiplatelet medication unless you receive clear instructions from an appropriate clinician.
This depends on the procedure and whether pain, numbness or weakness could affect safe control of the vehicle. Follow the specific advice given to you. If your ability to drive is impaired, do not drive.
Activity advice depends on the structure treated and the procedure performed. A period of relative rest may be recommended before gradually restarting rehabilitation or exercise. Follow your written aftercare plan.
There is no safe universal schedule. The decision depends on the diagnosis, target, response, tissue health, other treatment options and your medical history. Repeated injections are considered cautiously.
They may help selected patients when the headache pattern suggests irritation of a specific nerve, such as the greater occipital nerve. Headache has many causes, so assessment is essential before a nerve block is considered.
Sometimes. A targeted injection may help when persistent pain can be linked to a specific superficial nerve, scar, neuroma, abdominal wall plane or chest wall structure. Diffuse post-surgical pain without a clear target is less likely to benefit from a local procedure.
The result should be reviewed in context. Lack of benefit may lead to a revised diagnosis, further imaging, rehabilitation, a different treatment strategy or referral to another specialist.
Start with a specialist assessment. We will review your symptoms and relevant imaging, identify whether there is a sensible target, and explain the benefits, limitations and alternatives before treatment.