Dr Al-obaidi combines specialist expertise in spinal and musculoskeletal imaging with image-guided intervention. This allows scan findings, clinical assessment and precise procedural planning to be considered as one connected pathway.


Consultant-led spinal injections that use live X-ray imaging to guide treatment to the intended anatomical target, with careful assessment before the procedure and clear follow-up afterwards.
Identify the likely pain source
Confirm the target with imaging
Guide treatment precisely
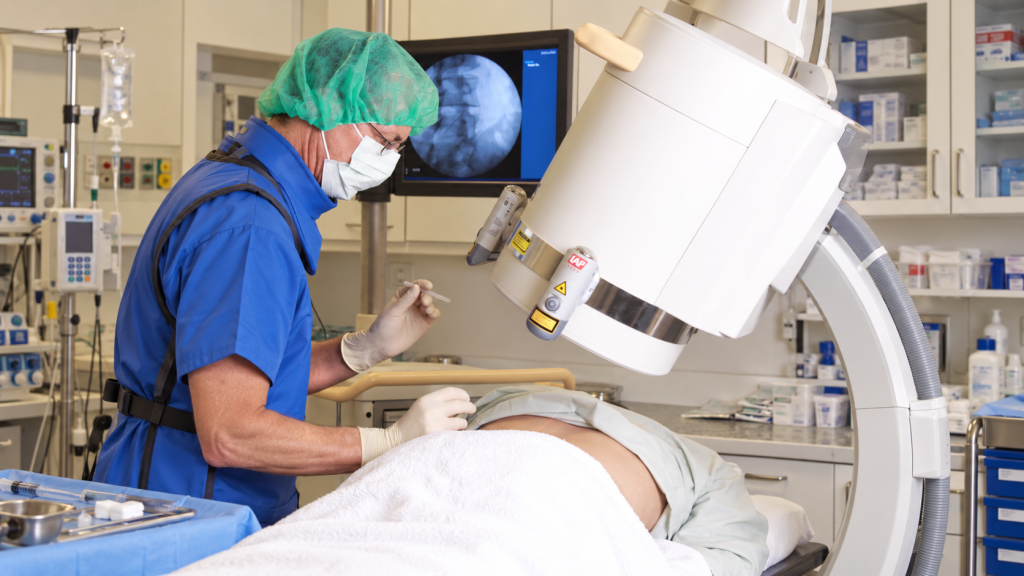
Fluoroscopy is a form of real-time X-ray imaging. It allows the consultant to see the relevant bony anatomy while carefully guiding a fine needle towards a selected spinal, nerve or joint target.
Depending on the procedure, a small amount of contrast may be used to help confirm the needle position and the expected spread before treatment is delivered.
The intended area can be identified rather than relying on surface landmarks alone.
The needle is advanced under live imaging with attention to surrounding structures.
The injection may be therapeutic, diagnostic, or both, depending on the clinical question.
Different procedures for different pain sources.
The correct procedure depends on your symptoms, examination and imaging. These injections are not interchangeable.
Medication is introduced into the epidural space through the sacrum to help selected lower back and leg pain linked to spinal nerve irritation.
A targeted injection into the sacroiliac joint, where the lower spine connects with the pelvis. It can help test whether this joint is contributing to pain and may also provide therapeutic relief.
A small amount of local anaesthetic is placed near the medial branch nerves that carry pain signals from the facet joints. The response helps assess whether these joints are a source of pain.
A targeted injection around a specific spinal nerve as it exits the spine. It may be used to investigate or treat selected nerve-related pain, such as symptoms travelling into the leg.
An injection may be considered when your symptoms, clinical findings and relevant imaging point towards a structure that can be targeted safely and meaningfully.
It is not suitable for every type of back pain, and an abnormal scan alone is not a reason to perform a procedure.
Diagnosis comes first.
If an injection is unlikely to help, if more information is needed, or if rehabilitation or another specialist is the better next step, we will explain that clearly.
A clear route from symptoms to a sensible plan.
Where appropriate, the key decisions are connected rather than divided between unrelated appointments.
Identity, health changes, medicines and consent are checked.
You are positioned carefully on the X-ray table.
The skin is cleaned and local anaesthetic is used.
Live X-ray imaging guides the needle to the target.
Contrast and medication are used as appropriate.
You are monitored briefly and given aftercare advice.
Good preparation is part of a safe procedure. Please read your appointment information carefully and tell the clinic if your health or medication has changed.
Bring an up-to-date list, including anticoagulants, antiplatelets and any previous reaction to medicines or contrast.
Tell us if you have diabetes, particularly if corticosteroid may be used, as it can temporarily affect blood glucose.
Contact the clinic if you have a fever, current infection, are taking antibiotics, or feel unwell before the appointment.
Tell us if you are pregnant or there is any possibility that you may be pregnant because X-rays are used.
Follow the procedure-specific advice supplied by the clinic. Requirements can vary, particularly if sedation is planned.
Potential benefits, with realistic expectations.
The aim is to create a useful change in pain, function or diagnostic understanding. No injection can guarantee a particular result.
Your consultant will discuss the purpose of the proposed procedure, reasonable alternatives and what would count as a useful response in your particular case.
The risks vary according to the injection, your health and your medication. Your consultant will explain the procedure-specific risks and answer questions before consent.
Serious complications are uncommon, but it is important that you know what to look out for.
Soreness, bruising or a short-lived flare of pain.
Numbness, weakness, dizziness or faintness can occur.
Flushing, sleep disturbance or a temporary rise in blood glucose.
Bleeding, infection, allergic reaction or severe headache.
Nerve injury or other neurological complication.
The injection may not improve the symptoms.
new or worsening weakness, new bladder or bowel difficulty, numbness around the saddle area, fever, increasing redness or swelling, or a severe persistent headache. Follow the emergency advice given by the clinic.
You will be given advice matched to your procedure. Temporary soreness is possible, and the effect of an injection can take time to become clear.
For diagnostic blocks, recording the timing and degree of change in your usual pain can be particularly important. This information helps decide the next step.
Activity, driving and medication advice can differ between procedures.
Note changes in your familiar pain and what you can do more easily.
Where advised, use the opportunity to progress rehabilitation.
Use the clinic or emergency contact advice supplied after treatment.
Assessment, imaging and intervention brought together.
Your procedure is planned in the context of your clinical problem, not treated as an isolated technical appointment.

Dr Al-obaidi combines specialist expertise in spinal and musculoskeletal imaging with image-guided intervention. This allows scan findings, clinical assessment and precise procedural planning to be considered as one connected pathway.

Dr Alaib assesses and manages spinal pain, nerve-related pain and other persistent pain presentations. He focuses on balanced non-surgical treatment planning and interventional procedures where these are appropriate.
Questions, answered clearly.
These answers are general. Your consultant and appointment information will provide advice specific to your procedure.
Local anaesthetic is used to numb the skin. You may feel pressure or brief discomfort during needle positioning or when medication is injected. Tell the clinical team if you are uncomfortable.
Many X-ray-guided procedures are performed with local anaesthetic while you are awake. Sedation is not always necessary. If it is being considered, the preparation and travel advice will be different and will be explained in advance.
The timing varies with the procedure and the number of targets. Allow time for safety checks, positioning, the procedure itself and a short period of observation afterwards.
Local anaesthetic may produce a quicker, temporary change. If corticosteroid is used, any benefit may take longer to become apparent. Some people do not experience meaningful improvement.
There is no reliable single answer. Relief may be brief, sustained for a period, or absent. A medial branch block is usually designed to provide temporary diagnostic information rather than lasting pain relief.
This needs an individual safety assessment. Tell the clinic exactly what you take and why. Do not stop anticoagulant or antiplatelet medication without specific instructions from an appropriate clinician.
Relevant imaging is often important, but the type and timing depend on the clinical question. Existing MRI, CT or X-ray imaging can be reviewed, and further imaging is arranged only when it is needed.
A lack of benefit can still be informative, particularly after a diagnostic procedure. The result is reviewed in context and may lead to rehabilitation, further assessment, a different treatment strategy or onward referral.
Fluoroscopy uses ionising radiation. Exposure is kept as low as reasonably practicable while obtaining the images needed to perform the procedure safely. Tell the clinic if you are pregnant or might be pregnant.
Start with a specialist consultation. We will review your symptoms, relevant imaging and previous treatment, then explain whether a procedure is appropriate and what it is intended to achieve.